
AI in Healthcare Apps in the UAE: Use Cases, Infrastructure, and Compliance
AI-driven tools are already streamlining diagnosis, treatment plans, and more. Discover how AI is revolutionizing healthcare by improving patient outcomes, driving efficiency, and what it takes to navigate the compliance requirements.
- AI Development
- Health & Wellness
October 06, 2026
 AI Overview
AI healthcare apps in the UAE use machine learning, computer vision, NLP, and predictive models to support diagnostics, patient engagement, remote monitoring, and hospital operations. To scale locally, they may need integration with Riayati, Malaffi, or NABIDH, FHIR/HL7 interoperability, UAE health-data controls, and clinical oversight. Validate performance locally before AI influences patient care.


In the UAE, AI healthcare applications make use of machine learning, computer vision, natural language processing, and predictive models in order to assist with diagnostics, patient engagement, remote monitoring, and hospital operations. To scale locally, they may need integration with Riayati, Malaffi, or NABIDH; FHIR/HL7 interoperability; UAE health-data controls; and documented clinical oversight. Organizations should validate performance on local data before AI influences patient care.
Healthcare organizations in the Emirates no longer need to debate whether to use AI in clinical and administrative procedures. The harder question is what a regulator will accept, what a national platform will connect to, and what a clinical governance committee will approve. Since late 2025, this question has become more specific: Abu Dhabi now has a binding standard for AI systems in licensed health organizations, and the three main health information platforms are linked electronically.
This article covers AI in healthcare applications in the UAE — the use cases with local traction, the infrastructure they connect to, the rules that constrain them, and what must be true before a model reaches production. For the broader global picture of adoption evidence, return on investment, and how hospital boards decide what to fund, see our separate analysis of AI solutions in healthcare.
How AI Healthcare Apps Connect to the UAE’s National Health Data Infrastructure
For an AI healthcare application to reach meaningful scale in the UAE, interoperability has to be a design decision rather than a later integration project. A model that cannot read a patient’s history across providers is limited to whatever a single facility holds, which is rarely enough to support the predictions it was built to make.
The UAE operates three major health data platforms, each with a different role. Riayati is the National Unified Medical Record, run by the Ministry of Health and Prevention. Malaffi is Abu Dhabi’s health information exchange. NABIDH is Dubai’s, operated under the Dubai Health Authority. They are not three national systems; they are one national record and two emirate-level exchanges, and together they form the backbone of the digital health UAE ecosystem. In 2023, the three authorities announced the successful integration of Riayati, Malaffi and NABIDH, a milestone in digital health transformation in the UAE that makes a patient record portable across emirate boundaries and a national data strategy realistic rather than aspirational.
When an application connects to these platforms through HL7 FHIR, it is able to access aggregated, longitudinal clinical data rather than just isolated records from individual encounters. This change has an impact on what is technically feasible:
Predictive analytics that flags patients at elevated risk early enough for the prediction to be actionable, which depends on data engineering work to make cross-provider records usable.
Personalized treatment support, where models weigh a patient’s documented history, lab results, and comorbidities instead of a single visit.
Population health monitoring, where trends are visible at community scale and can inform public health decisions.
Is Integration With Riayati, Malaffi, or NABIDH Actually Mandatory?
Most vendor content answers this badly, implying that every application must connect to everything. It depends on the facility, the emirate, and the use case.
Integration obligations attach to licensed healthcare facilities, not to software in the abstract. A facility licensed by the Dubai Health Authority falls under the NABIDH program, whose Standards for Interoperability and Data Exchange — version 2, issued April 2025 and effective 2 July 2025 — name HL7 v2 as the recommended standard for accessing and submitting data, and expect health information systems to support FHIR and IHE messaging profiles. A facility licensed in Abu Dhabi operates within Malaffi. An application handling patient records on such a facility’s behalf inherits those obligations. A wellness app that never touches a licensed provider’s clinical record generally does not.
The integration question usually gets answered in the wrong room. Teams treat it as an architecture decision when it is really settled by the customer’s license and emirate. Building for FHIR early costs very little. Discovering the requirement mid-procurement costs a release.



That is why integration scope belongs in the discovery conversation rather than at architecture review, and why a clinical platform modernization project starts at the data and workflow layer rather than the interface.
AI in Healthcare UAE: Data and Regulatory Requirements
Compliance in the UAE health sector is often described in absolute terms that don’t hold up when you meet the actual instruments. Four points matter most for anyone building or procuring an AI healthcare application, and together they govern the use of AI in healthcare across the country.
Health data is governed by sector-specific law, not only by general data protection. The main legislation in this area is Federal Law No. 2 of 2019 on the use of information and communication technology in health fields, which applies across the UAE, including free zones, and requires health information to remain confidential, accurate, and available to authorized parties. The UAE government’s summary of the legal framework for ICT in the health sector is the clearest official starting point. The Personal Data Protection Law, Federal Decree-Law No. 45 of 2021, expressly classifies data relating to a person’s health as sensitive personal data and is relevant, but it does not displace the health-specific regime.
Data localization is a default with defined exceptions, not an absolute ban. The default position is that health data generated in the UAE is stored in the UAE. Ministerial Decision No. 51 of 2021 then sets out ten circumstances in which health data may be stored or transferred abroad, including treatment of a patient overseas, laboratory samples, approved scientific research, insurance claims, telemedicine, pharmacovigilance reporting, government cooperation, and transfers requested by the patient. In each of these cases, conditions apply, such as encryption, anonymization, retaining a local copy, or obtaining written consent. When designing systems, it is necessary to plan for processing within the country, and any transfer across borders must be treated as a formally documented exception based on a specific legal basis.
Abu Dhabi now has a binding AI standard. The Department of Health’s Responsible Artificial Intelligence Standard, effective October 2025, applies to DoH entities and the wider Abu Dhabi healthcare ecosystem and covers AI whether developed internally, procured from a vendor, or produced through a research collaboration, across clinical, financial, and administrative functions. It requires the classification of risks into four categories, with the highest category being banned from deployment and high-risk systems being subject to conformity assessments; human oversight with documented escalation protocols, override mechanisms, and audit trails, keeping clinicians as the final decision-makers; compute and storage infrastructure inside the UAE for both active and disaster recovery sites, with remote development and support access originating inside the country; and continuous post-deployment monitoring with alerting for performance degradation. These are hard architectural requirements, not policy goals, and should be included in a build estimate prior to choosing a model.
Dubai regulates AI through the DHA. The Dubai Health Authority issued its Policy for Use of Artificial Intelligence in Healthcare in the Emirate of Dubai by circular in August 2021, directed at DHA-licensed professionals and facilities. Subsequent DHA circular guidance on AI and data protection extends to AI developers working with Dubai-based data and to pharmaceutical manufacturers and health insurers using AI. Its recurring requirements include systems that are fair and free of bias; disclosure of AI-enabled functions, validation processes, the datasets used, and the role of clinicians in the decision; controlled access to patient information; and design that allows a human to intervene and reverse a decision.
Two common mistakes are worth mentioning. HIPAA is a United States law, not a requirement in the UAE; it applies only when a project falls within its scope, for example, when handling data on behalf of a US covered entity. ISO 27001 is a voluntary certification that can show that an organization has a mature security posture, but it is not a regulation in the UAE, and possessing the certification does not mean that compliance with any regulation has been achieved.
Applications that are designed with local data residency, complete documentation of oversight, and native interoperability in mind are able to move through the procurement and clinical governance processes more quickly since the architecture has already addressed the questions that a governance committee would ask. Partners providing AI development services into this market are evaluated on exactly that readiness.
Six AI Healthcare Use Cases Already Relevant in the UAE
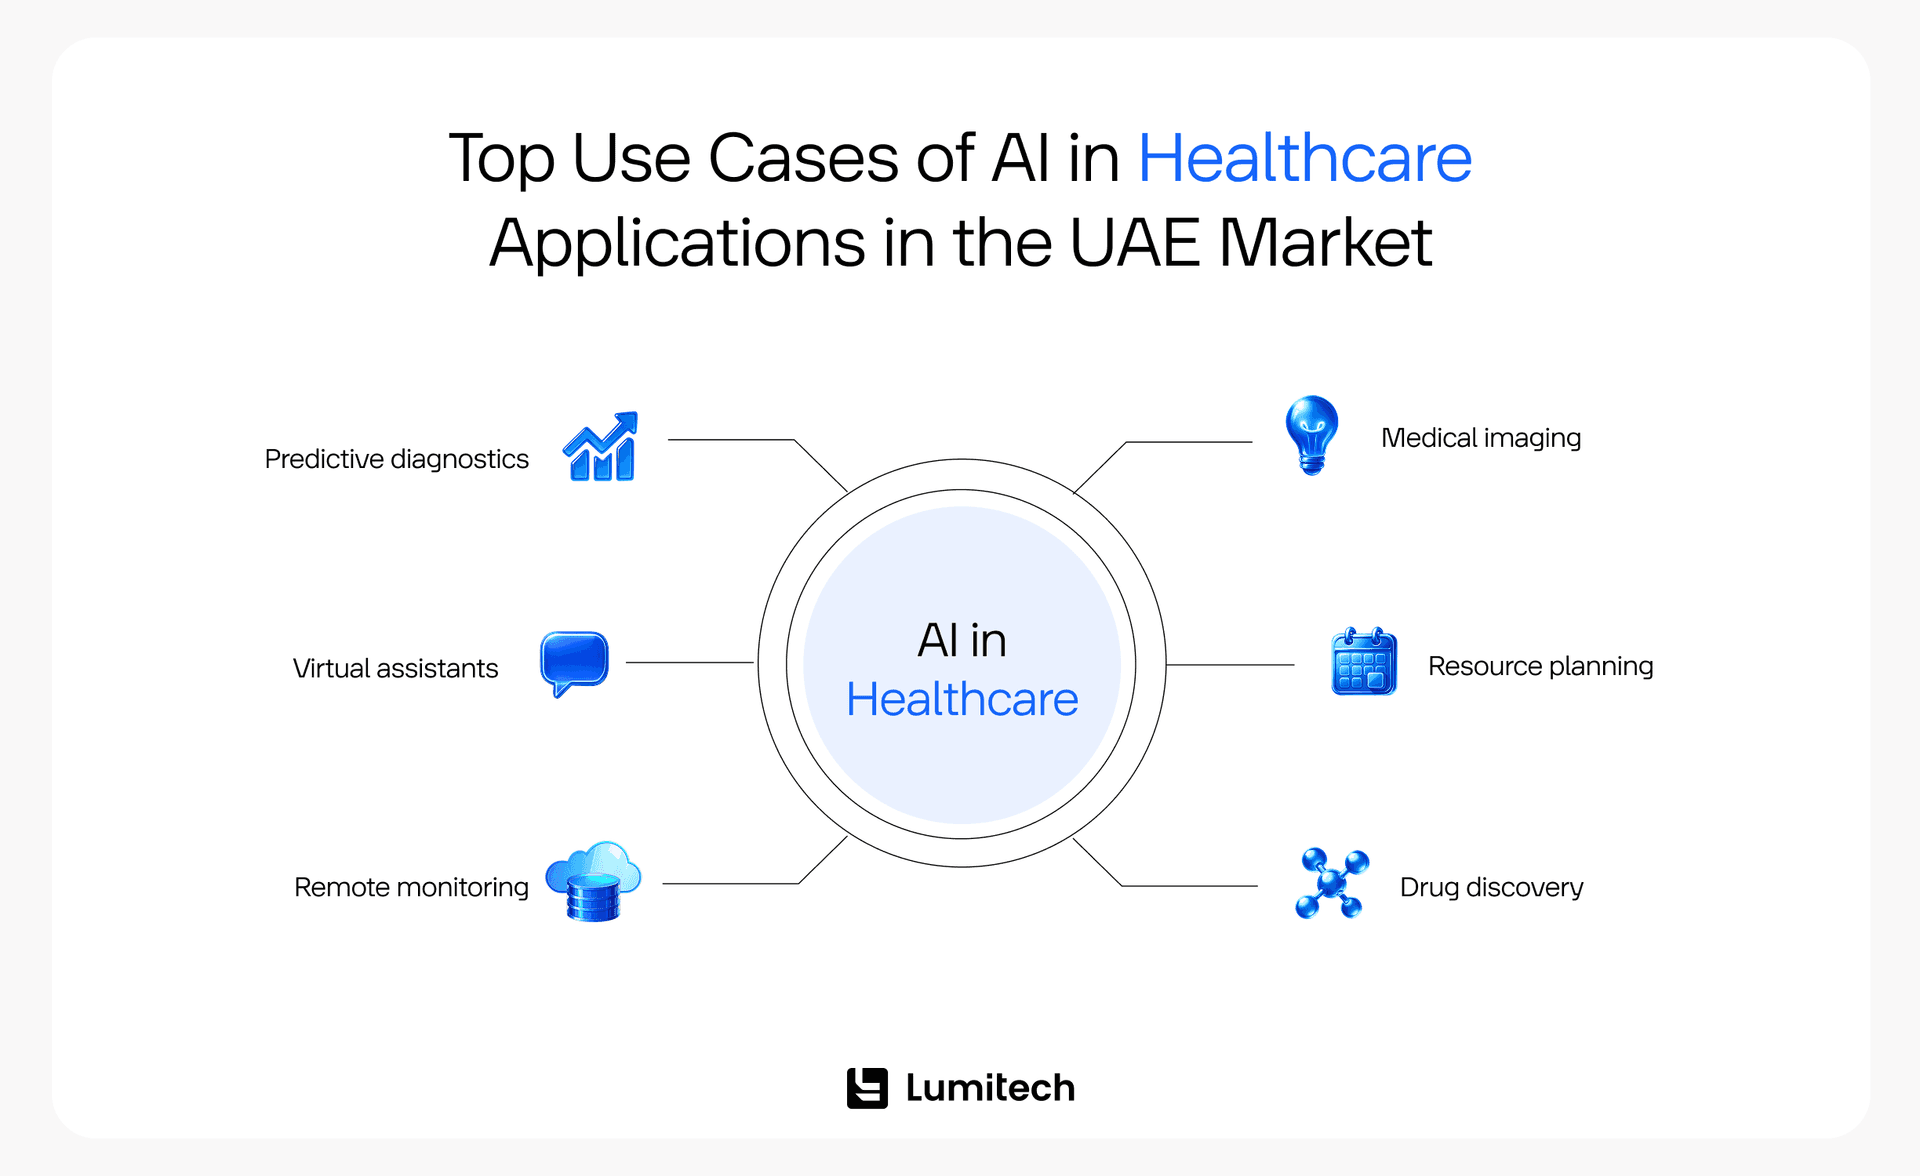
The UAE market has moved from speculative pilots toward deployments with published evidence behind them, though the gap between the two is still wider than most vendor material admits. The six AI applications in healthcare below are ordered roughly by how much local proof exists, strongest first.
How Is AI Used in Healthcare in the UAE?
AI is used in the UAE across four broad areas: imaging and population screening, where the strongest local evidence exists; patient-facing triage and virtual assistants; remote monitoring of chronic and high-risk patients; and hospital operations such as capacity and scheduling forecasting. Clinical deployments concentrate where a model’s output can be checked against a definitive test, and a clinician stays in the decision path. Much of what is described as deployed AI in healthcare is still at pilot stage — a distinction worth probing in any vendor claim.
Predictive Diagnostics and Early Disease Detection
Among the applications of artificial intelligence in healthcare, predictive diagnostics has the clearest local evidence base. Algorithms identify abnormalities in imaging, pathology, or genomic data before symptoms present, shifting a screening program from confirming disease to finding it.
The strongest documented UAE example is AIRIS-TB, developed by M42 and deployed at the Capital Health Screening Center in Abu Dhabi. A population-scale study published in npj Digital Medicine in July 2025 evaluated it on approximately 1.04 million chest X-rays, reporting an AUC of 98.51% and automation of roughly 80% of routine chest X-ray reporting at the study’s optimal operating threshold, falling to around 40% at its more conservative safe setting. The tuberculosis-specific false negative rate was 0% at the safe setting and 0.11% at the optimal setting; the overall false negative rate for all findings was 1.57%, compared to 1.85% for the radiologists who carried out the reporting.
The number worth understanding is not the 80% but the operating threshold that produces it. If the same system is adjusted to achieve a lower miss rate, then it will automate only half the amount of work. That trade-off between throughput and caution is the real design decision in any screening deployment, and it belongs to clinical governance, not engineering. Note the scope too: this is tuberculosis screening in a large mandatory-screening population with TB prevalence below 0.5%, not general-purpose radiology triage.
Core technologies: deep learning, particularly convolutional neural networks for image analysis; genomic sequence interpreters.
Medical Imaging and Computer Vision
Beyond screening programs, computer vision helps radiologists detect fractures, tumors, and lung pathology, usually by prioritizing studies rather than drawing conclusions.
The screening for diabetic retinopathy fits the region well. The IDF Diabetes Atlas puts age-standardized diabetes prevalence among adults in the Middle East and North Africa at 19.9%, the highest of any IDF region, with around 37% of cases undiagnosed. Automated analysis of retinal images identifies possible cases at the point of care, allowing specialists to focus their time on confirmed cases and patients with more complex conditions. However, the maturity of local deployment varies by provider, so it should be seen as an established use case rather than a definitive local success story.
Core technologies: computer vision, pattern recognition and anomaly detection models, integration with the DICOM standard for imaging data exchange.
Virtual Health Assistants and AI Chatbots
Providers use conversational systems for patient inquiries, symptom checking, and appointment routing — a front door that directs patients to the appropriate and often less expensive level of care. Arabic-language capability is a functional requirement here, not a localization afterthought, and it materially affects model selection.
The same natural language processing stack addresses a problem that attracts less attention than diagnostics but costs more in aggregate: documentation. AI medical documentation software that drafts clinical notes from an encounter targets administrative workload directly, which is usually where AI returns value earliest. Mental health is an adjacent and more demanding design problem, where escalation paths and clinical safety constraints are far stricter than in general triage — as in our work on a mental health app built for real-time support, which connects users to human listeners rather than to a model.
Core technologies: natural language processing, clinical large language models, EHR and scheduling API integration. Teams building in this area typically need AI chatbot development capability alongside clinical workflow knowledge.
Remote Patient Monitoring (RPM) and Wearable Data Insights
Rising chronic disease prevalence has pushed UAE providers toward connected monitoring, where wearables and home devices stream vitals continuously, and AI in healthcare applications flag deviations from a patient’s baseline before deterioration becomes acute.
Evidence for improved outcomes is real but narrower than commonly claimed. A study published in The American Journal of Managed Care in March 2025 reported that heart failure readmissions at an urban safety-net hospital fell from 27.9% to 23.9% after introducing a random-forest readmission risk model with an AUC of 0.72 alongside EHR-integrated discharge decision support and a multidisciplinary follow-up team. That is a four-percentage-point absolute reduction, in one condition, in a US setting, produced by a model plus a redesigned care pathway — and the authors are explicit that the model alone would not have produced it. It supports the view that risk prediction can reduce readmissions. It is not evidence that a model alone delivers a fixed percentage improvement, and a vendor presenting it that way is overselling.
Core technologies: IoT integration protocols, time-series analysis, event prediction models.
Predictive Resource Planning for Hospitals
Operational forecasting is where AI most often pays for itself without touching clinical decision-making, making it the lowest-risk entry point under the governance regimes above. Models use admission history, seasonality, and scheduling data to forecast patient flow and anticipate demand in units such as ICUs or operating rooms.
The narrower version of this problem is appointment attendance. Patient no-show prediction, covered in our guide to AI no-show prediction for clinics, uses historical booking behavior to forecast which appointments will be missed, enabling targeted reminders or controlled overbooking. Read the equity considerations in that analysis first: models trained on historical attendance can encode access disparities if used to deprioritize patients rather than support them.
Deployments in this category across the UAE remain largely internal or at pilot stage, with few quantified public results.
Core technologies: predictive analytics, time-series forecasting, EMR and ERP integration.
Drug Discovery and Personalized Treatment
In terms of research, organizations are using AI for the purpose of precision medicine, including conducting multi-omic studies on the Emirati population in order to detect population-specific markers for which globally derived drug models may not transfer smoothly. The benefits in this area are long-term in nature, relating to intellectual property, trial efficiency, and research positioning, rather than providing a short-term operational return, and therefore fall outside the scope of most application development programs.
Core technologies: Computational Biology, Genomic Deep Learning Models, Precision Medicine Platforms.
The Technology and Security Stack Behind AI Healthcare Apps
These use cases share an infrastructure layer, and its quality determines whether a model that performs well in evaluation still performs well eighteen months into production. The table below maps the core technologies behind AI applications in healthcare to the local implementation considerations each raises and the controls that address them.
Technology | Purpose in healthcare | UAE implementation consideration | Main control |
|---|---|---|---|
Deep learning frameworks | Training and serving models for imaging and text | Compute and storage siting, including disaster recovery | In-country infrastructure per the DoH Responsible AI Standard |
Computer vision | Interpreting X-rays, CT, MRI, retinal images, pathology slides | Operating threshold determines automation rate and miss rate | Clinical governance sign-off on threshold selection |
Clinical large language models | Summarizing notes, drafting discharge instructions, decision support | Arabic-language performance; hallucination risk in clinical text | Clinician review before any output enters the record |
Predictive analytics engines | Risk scores, readmission, resource utilization | Local population may differ from training cohort | Validation on local data before clinical influence |
Natural language processing | Converting dictation and patient messages into structured EHR data | Data classed as sensitive under the PDPL | Access control, audit logging, de-identification where feasible |
The recurring theme is that the control is organizational at least as often as it is technical. A threshold choice, a validation requirement, and a review step are decisions the provider owns, which is why AI procurement in this market increasingly resembles medical device procurement.
Two infrastructure points are widely misrepresented and deserve direct statements. First, region availability is not regulatory approval: hyperscalers operate UAE regions and offer healthcare-oriented configurations, but no regulator certifies a cloud provider as compliant on a customer’s behalf, and the obligation stays with the licensed entity. Second, a deployed model is not a finished model. Drift, population shift between the training cohort and the served population, and automation bias — clinicians deferring to a system they have stopped scrutinizing — are common failure modes, and catching them requires the monitoring the Abu Dhabi standard now mandates. That is the substance of MLOps and AI infrastructure work, and it is routinely underfunded relative to model development.
These requirements shape the application layer as much as the model layer. For healthcare app development UAE teams, that means healthcare mobile development services built around data residency and audit requirements from the first sprint rather than at hardening. When real patient records cannot be moved for development and testing, synthetic data generation can produce datasets that preserve statistical structure without exposing identifiable information—useful for building, though it doesn’t remove the need to validate on real local data before clinical use.
Overcoming Barriers to AI Adoption in UAE Healthcare
Technical and regulatory readiness solves only part of the problem. The remaining barriers are cost perception, clinician trust, and the absence of a credible path from pilot to production. A phased approach addresses all three, and it works equally well for health and wellness software development projects, where you can validate outcomes with a small user group before scaling.
Start Small and Prove Value
The most effective way to begin using AI in healthcare is not organization-wide transformation but a narrow, high-impact pilot with a defined success measure. An AI readiness audit establishes which use case can actually clear governance before any build starts. A proof-of-concept (PoC) then lets a hospital test one real outcome — diagnostic turnaround time, documentation burden, no-show rate — before committing to a rollout. Phased implementation limits financial exposure and produces the internal evidence the next phase has to be argued from.
Validate on Local Data Before Clinical Influence
A model’s published performance was measured on someone else’s population. Where the served population differs in demographics, disease prevalence, or documentation practice, performance can degrade in ways aggregate metrics conceal. It is good practice to carry out local validation before any AI output is used to make a clinical decision, and in Abu Dhabi this is regarded as a regulatory requirement. Budget and schedule it explicitly: retrofitting a validation study after a governance committee asks for one is a leading cause of stalled deployments.
Co-Develop With Clinicians
Adoption depends on clinical teams being collaborators, not recipients. Involving physicians, nurses, and administrators in early design sessions surfaces workflow realities that requirements documents miss, and builds the trust that determines whether a deployed system is used at all. This is not a soft consideration: a well-performing model that clinicians route around delivers nothing.

Navigate Data and Compliance Constraints
The UAE’s unified medical record infrastructure has improved data quality and availability, enabling better models. It also means developers work inside a defined regulatory perimeter set by MOHAP, the Department of Health in Abu Dhabi, and the DHA. For the wider regional picture, our analysis of AI governance in MENA examines how regulated organizations approach AI release approval across the region.
Ensure Explainability and Public Trust
Transparency is a requirement in both the Dubai and Abu Dhabi frameworks. The NIST AI Risk Management Framework draws the distinction that matters in practice: explainability describes the mechanism behind a system’s operation, while interpretability describes what its output means in the context it was built for. Clinicians usually need the second. Public communication matters alongside it: describing AI as augmenting clinical expertise rather than replacing it is accurate, and accuracy is what sustains trust when a system eventually gets something wrong.
Wrapping Up
The UAE has built the infrastructure and, more recently, the regulatory scaffolding for artificial intelligence in healthcare at a pace few markets have matched. Riayati, Malaffi, and NABIDH are integrated; Abu Dhabi has a binding AI standard with real architectural implications; Dubai has an established policy framework. The constraints are knowable in advance, which is a considerable advantage for teams willing to design against them.
What separates AI healthcare UAE programs that reach production from those that stall is rarely model quality. It is whether data residency, clinical oversight, interoperability, and local validation were treated as design inputs or discovered late as obstacles. Organizations assessing suppliers may also find our buyer’s guide to AI companies in Dubai and the UAE useful. The teams that succeed here understand both the technology and the governance environment it operates in — and that combination, more than any individual model, turns a promising use case into a system clinicians trust.



